







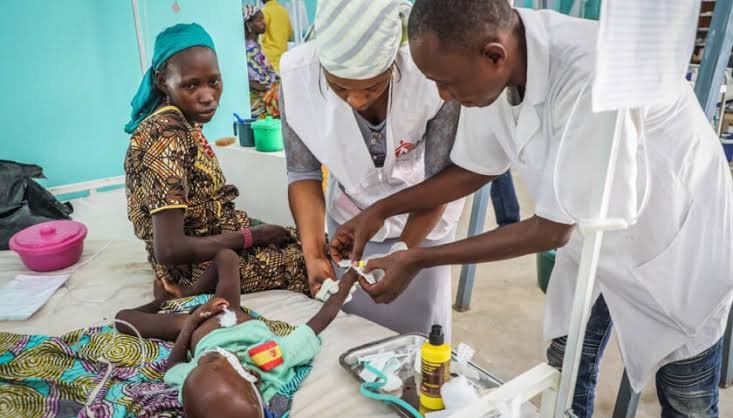
Nigeria has released more than ₦422 billion for its Basic Health Care Provision Fund (BHCPF) since 2019, supporting the revitalisation of primary healthcare centres, recruitment of health workers and expansion of health insurance coverage.
However, concerns over financial accountability, procurement delays, inadequate workforce funding and the long-term financing of healthcare services are raising questions about whether the progress can be sustained.
The challenges were highlighted at the 2026 Health Sector Joint Annual Review (JAR) in Abuja, where government agencies and development partners reviewed the implementation of the programme and identified areas requiring urgent attention.
For millions of Nigerians, particularly those in rural communities, primary healthcare centres remain the first point of access to medical services, including antenatal care, childbirth, immunisation and treatment of common illnesses.
Their ability to deliver these services depends on functional facilities, qualified health workers, essential medicines and reliable operational funding.
Established under Section 11 of the National Health Act 2014, the BHCPF was designed to improve access to basic healthcare and reduce financial barriers for poor and vulnerable Nigerians.
Yet, the latest programme assessment suggests that releasing more money alone may not guarantee lasting improvements.
Nigeria Releases ₦422.3bn, but Accountability Gaps Persist
Between 2019 and October 2026, cumulative releases to the BHCPF reached ₦422.3 billion, while ₦323.6 billion had been disbursed to implementing gateways, representing approximately 76 per cent of the total releases.
Presenting the programme overview, Secretary of the BHCPF Ministerial Oversight Committee at the Federal Ministry of Health and Social Welfare, Dr Uzoma Nwankwo, explained that the fund receives an annual allocation of at least one per cent of the Consolidated Revenue Fund.
It also receives contributions from development partners and other sources, including the private sector.
Despite the scale of funding, financial reporting and accountability remain major concerns.
Findings presented during a session titled “Learnings from Nigeria’s Pro-Poor Programme as a Means of Advancing Universal Health Coverage” showed that only 53 per cent of participating states submitted complete financial retirement packages.
Although 78 per cent submitted bank statements and payment vouchers or receipts, the figures point to gaps in financial documentation and reporting.
The presentation, moderated by Senior Health Finance and Public Financial Management Specialist at Results for Development Institute (R4D), Dr Stanley Ezenwa, also identified procurement challenges across 10 states.
These included delayed deliveries in eight states, incomplete supplies in six states and inflated costs in seven states.
In one state, 29 out of 57 facilities reportedly carried out activities that were not included in their approved business plans, while 22 facilities said they experienced external influence on their plans.
The findings raise questions about how effectively public funds are monitored and whether resources allocated to frontline facilities are being used as intended.
Over 3,000 Primary Healthcare Centres Revitalised
Despite the implementation challenges, the National Primary Health Care Development Agency (NPHCDA) reported improvements in facility infrastructure and functionality.
The agency’s Director of Special Duties and National Programme Lead for BHCPF, Dr Uzoamaka Epundu, disclosed that its gateway had disbursed ₦113 billion since the programme began.
Of this amount, ₦72.6 billion went directly to healthcare facilities through Direct Facility Financing (DFF), while ₦24.3 billion supported the recruitment of Skilled Birth Attendants (SBAs) and Community-Based Health Workers (CBHWs).
Epundu said more than 3,000 primary healthcare centres were revitalised between 2024 and 2026, while 8,309 facilities across the 36 states and the Federal Capital Territory currently receive BHCPF support.
The revitalised facilities include:
- 2,471 supported through the BHCPF.
- 708 supported by state governments.
- 156 supported through the IMPACT programme.
- 249 supported through other sources, including development partners and the private sector.
Another 850 facilities were undergoing revitalisation at the time of the presentation.
The agency also reported an improvement in the number of facilities meeting Level Two functionality standards.
Facilities meeting the standard increased from 1,748, representing 21 per cent, in the second quarter of 2024 to 3,202, or 39 per cent, in the third quarter of 2026.
Meanwhile, partially functional facilities declined from 1,165, representing 14 per cent, to 209, or three per cent.
Level Two functionality requires facilities to operate around the clock, have skilled birth attendants, functional infrastructure and essential equipment, reliable electricity with solar backup, and provide services such as antenatal care, facility-based deliveries and routine immunisation.
Epundu also said BHCPF-supported facilities performed better than non-supported facilities in selected service indicators, including antenatal care visits, skilled birth attendance and administration of the third dose of pentavalent vaccine to children under one year.
However, maintaining these improvements will require consistent funding for operations, adequate staffing, equipment maintenance and essential medicines.
Who Will Pay Health Workers When Federal Support Changes?
One of the major questions surrounding the programme is the long-term financing of health workers recruited through the BHCPF.
The fund has supported the recruitment of skilled birth attendants and community-based health workers to address staffing shortages at primary healthcare facilities.
However, concerns remain over what happens when programme financing is reduced or withdrawn.
Under the existing arrangement, states are expected to gradually absorb eligible workers into their payrolls to ensure continuity of healthcare services.
Epundu said NPHCDA was adopting a phased financing and progressive absorption model to address the challenge.
She urged state governments to release their 25 per cent counterpart funding, integrate eligible health workers into their payrolls and strengthen supervision of healthcare facilities.
The issue is particularly important because revitalised facilities cannot provide round-the-clock services, safe deliveries, immunisation and emergency care without sufficient numbers of trained health workers.
Without clear budgetary commitments from state governments, some facilities could struggle to retain the personnel recruited to improve service delivery.
Epundu stressed that the BHCPF should complement, rather than replace, funding from state and local governments.
She also highlighted the need for frontline health workers to be adequately trained and available to manage facility resources.
Health Insurance Enrolment Rises to 24.09 Million
Beyond infrastructure and staffing, the BHCPF has contributed to expanding health insurance coverage, particularly among vulnerable Nigerians.
The Director of the Informal Sector Department at the National Health Insurance Authority (NHIA), Dr Nnennaya Kalu-Umeh, said overall health insurance enrolment increased from approximately 16.8 million in 2023 to 24.09 million in 2026.
BHCPF-supported enrolment also rose from 1.8 million to 3.18 million within the period.
Women accounted for 64 per cent of BHCPF beneficiaries, while older persons represented 15 per cent and children below five years accounted for nine per cent.
Kalu-Umeh explained that the programme provides the Basic Minimum Package of Health Services at no cost to enrolled beneficiaries through accredited primary and secondary healthcare facilities.
Its targeted interventions include Comprehensive Emergency Obstetric and Newborn Care, treatment for women living with obstetric fistula and healthcare support for key populations.
She reported that the emergency obstetric and newborn care intervention covered 88,662 maternal beneficiaries and 11,970 newborns.
The Fistula-Free programme recorded 6,103 beneficiaries, while the intervention for key populations, including people living with HIV and tuberculosis, reached 71,229 beneficiaries.
Despite the progress, Kalu-Umeh identified inadequate funding relative to the level of need, delayed disbursements and the absence of a comprehensive exit strategy for BHCPF enrollees as major challenges.
This raises concerns about how vulnerable beneficiaries will maintain access to healthcare if existing programme funding arrangements change.
NIN, Digital Monitoring and Other BHCPF 2.0 Reforms
To improve programme management, the government is introducing reforms under BHCPF 2.0.
Kalu-Umeh said the National Identification Number (NIN) would serve as a unique identifier for beneficiaries to strengthen verification and improve enrolment and disbursement management.
Other proposed improvements include harmonised facility accreditation standards, stronger financial management, improved monitoring and evaluation, performance incentives for State Social Health Insurance Agencies, training, audits and sanctions.
The reforms are intended to improve transparency, reduce inefficiencies and ensure that healthcare resources reach eligible beneficiaries and facilities.
What Happens Next?
As the BHCPF expands, the responsibility for sustaining its gains increasingly rests on stronger cooperation between federal and state governments.
NPHCDA has identified several priorities for 2027, including extending Direct Facility Financing to another 5,212 facilities, transitioning to digital financial management, introducing pooled procurement of medicines and absorbing eligible ad hoc health workers into an optimised recruitment model.
These plans will require state governments to demonstrate stronger ownership of primary healthcare through counterpart funding, workforce financing, infrastructure maintenance and improved supervision.
The NHIA has also called attention to funding gaps and delayed disbursements, while the National Emergency Medical Services and Ambulance System (NEMSAS) has emphasised the need for better emergency communication systems and stronger verification mechanisms.
For the Nigeria Centre for Disease Control and Prevention (NCDC), sustained investment in subnational disease surveillance and outbreak response remains important for protecting vulnerable communities.
Ultimately, the success of the BHCPF will not be determined only by the amount of money released, the number of facilities renovated or the number of people enrolled in health insurance.
For ordinary Nigerians, the real test will be whether medicines are available when needed, qualified health workers remain at their posts, emergency referrals happen on time and essential healthcare can be accessed without exposing families to financial hardship.
The ₦422.3 billion released to the programme represents a significant public investment. However, transparent financial management, efficient procurement, reliable workforce funding and stronger state government ownership will be critical to ensuring that the improvements translate into lasting healthcare services.
Without these measures, the country could struggle to sustain the gains made in primary healthcare, even as the demand for affordable and accessible medical services continues to grow.



